
Health
Man Sues Atlanta Hospital After Skull Fragment Is Lost, Leading To Medical And Financial Nightmare

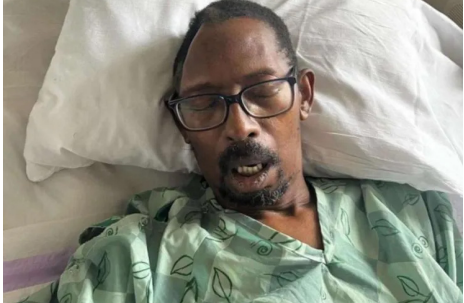
A Georgia man, Fernando Cluster, is suing Emory University Hospital Midtown in Atlanta after a shocking incident where a piece of his skull, removed during a routine medical procedure, was allegedly lost by hospital staff. The ordeal began in September 2022, when Cluster was admitted to the hospital for treatment of an intracerebral hemorrhage, commonly known as a brain bleed. Doctors determine that a 4.7-by-6 inch section of his skull needed to be temporarily removed to relieve pressure on his brain.
However, when Cluster returned to the hospital two months later to have the skull fragment reattached, the hospital was unable to locate it. According to an August 8 complaint obtained by the Atlanta Journal-Constitution, hospital staff searched a freezer where bone flaps are stored but could not find the one identified as belonging to Cluster. Instead, they discovered several unidentified bone fragments, none of which could be confirmed as his.
With a significant portion of his skull missing and no bone to replace it, Cluster’s scheduled surgery was abruptly canceled. The hospital then fabricated a synthetic piece of skull, which was eventually implanted at the end of November 2022. To Cluster’s shock, he was billed over $19,000 for the synthetic replacement—this despite the hospital allegedly losing the original bone.
Read also : New Jersey Woman Sues Funeral Home For Negligence After Father’s Ashes Found In Basement Decades Later
The situation worsened when Cluster developed an infection following the implantation of the synthetic bone, requiring additional surgery and forcing him to take time off work. By the end of his medical ordeal, his total hospital bill had ballooned to over $146,800. Despite the hospital’s apparent negligence, Cluster and his wife were not offered any financial relief for the costs they incurred.
Cluster’s attorney, Chloe Dallaire, expressed the family’s deep frustration, stating, “While my clients are obviously upset that they and their insurance company were billed for the costs related to Emory’s negligence, their primary concern is the egregiousness of the hospital losing a part of his body and then showing a flippant attitude about it afterward.”
Cluster and his wife are now seeking compensation from the hospital for their medical bills and the emotional distress caused by the incident. The lawsuit highlights serious concerns about hospital management and patient care, raising questions about how such a critical error could occur and the subsequent handling of the situation.



Trump Proposes Five-Way Split of Childhood Vaccines
President Donald Trump has proposed splitting some childhood vaccines into five separate doses administered six months apart, a plan that vaccine experts say could leave children inadequately protected if the individual doses contain too little vaccine.
Trump made the proposal on Friday while speaking about his administration’s plans to alter the United States childhood immunisation schedule.
He said children could receive doses labelled one through five, with each containing what he described as about 20 per cent of the usual amount.
“Instead of a child going in and having a tremendous amount of different vaccines pumped into a big proportion of the body … we’re going to recommend that they do five doses marked one, two, three, four, five and that they be given in six-month intervals,” Trump said.
Trump did not identify all the vaccines that would be affected. He specifically referred to the polio vaccine, which he described as having been “amazing”.
However, vaccine specialist Dr Paul Offit, director of the Vaccine Education Centre at the Children’s Hospital of Philadelphia, said the proposed approach would not provide the intended protection.
Offit explained that vaccines are developed through dose-response studies to determine the smallest quantity capable of producing a protective immune response.
“You don’t want to give too much, where you know you don’t need all that, and you don’t want to give too little,” he said.
He told CNN that administering vaccines at doses below the level required to generate an immune response could make them ineffective rather than safer.
Trump also linked the proposed changes to autism, saying he expected them to lead to a “massive reduction” in autism.
However, decades of scientific research have found no causal link between childhood vaccines and autism.
The President’s comments came amid broader efforts by his administration to alter federal childhood vaccination policy.
In August, Trump signed an executive order seeking changes to the childhood immunisation schedule, including separating the measles, mumps and rubella vaccine into individual shots.
The administration has argued that the changes would reduce the number of vaccines given to children and address concerns about the existing schedule.
Health and Human Services Secretary Robert F. Kennedy Jr., who was with Trump as he outlined the proposal, has also backed changes to federal vaccine policy.
Kennedy spoke on Thursday at a conference organised by Children’s Health Defense, an organisation associated with vaccine scepticism.

DRC gets 70,000 Ebola vaccine doses as trial targets Bundibugyo virus
The Democratic Republic of Congo has received 70,000 doses of the Ervebo Ebola vaccine from the global vaccine stockpile as health authorities intensify efforts to contain an outbreak of Bundibugyo virus disease.
The doses were released by the International Coordinating Group on Vaccine Provision following a request from the DRC government last week.
The development comes amid uncertainty over the effectiveness of Ervebo against the Bundibugyo strain, which is different from the Zaire ebolavirus for which the vaccine was originally developed and licensed.
Of the 70,000 doses, 20,000 have been allocated for a Phase 3 clinical trial designed to assess the vaccine’s potential impact against the Bundibugyo virus, while 50,000 doses will be administered to frontline and health workers in line with recommendations from the World Health Organisation’s Strategic Advisory Group of Experts on Immunization.
The effectiveness of Ervebo against Bundibugyo virus in humans is currently unknown.
However, preliminary laboratory and animal studies have suggested that the vaccine could offer some protection, prompting researchers to investigate its potential through the clinical trial.
The trial is expected to generate evidence that could guide future decisions on the use of Ervebo in outbreaks involving the Bundibugyo strain.
Health authorities have also stressed the importance of informed consent, saying people offered the vaccine must be adequately informed about its potential risks, benefits and limitations in relation to the current outbreak.
The ICG is made up of the WHO, International Federation of Red Cross and Red Crescent Societies, Médecins Sans Frontières and UNICEF, while Gavi, the Vaccine Alliance, funds the global vaccine stockpile.
The WHO and Africa Centres for Disease Control and Prevention welcomed the allocation, supporting the DRC’s efforts to protect affected communities and contain the outbreak through a community-led response.
Both organisations said they would continue to support the DRC government in protecting communities, saving lives and generating scientific evidence that could strengthen Africa’s preparedness for future viral outbreaks.
The Bundibugyo outbreak has renewed attention on the need for effective vaccines and rapid scientific responses to emerging infectious diseases, with the outcome of the DRC trial expected to provide important information for future outbreak control.
Africa CDC, WHO demand urgent scale-up of DRC Ebola response
The Africa Centres for Disease Control and Prevention and the World Health Organisation have called for an urgent scale-up of the community-led response to the Ebola outbreak in the Democratic Republic of the Congo.
The organisations said the response must focus on early detection, contact tracing, access to treatment, protection of frontline health workers and faster deployment of resources to affected communities.
The call followed a joint high-level mission to Uganda and the DRC on August 4 and 5, led by the WHO Director-General, Dr Tedros Adhanom Ghebreyesus; Director-General of Africa CDC, Dr Jean Kaseya; and WHO Regional Director for Africa, Dr Mohamed Janabi.
The delegation visited Kampala, Bunia and Kinshasa, where it held discussions with government officials, response coordinators, health workers, community representatives and development partners.
In Uganda, the delegation commended the country for successfully containing local transmission after it declared the end of its outbreak on July 28.
Uganda recorded 20 confirmed cases and two deaths, while all identified contacts completed their follow-up.
The organisations said Uganda’s experience demonstrated the importance of early detection, rapid contact tracing, coordinated government action, community engagement and effective cross-border surveillance.
However, they warned that continued transmission in the DRC meant neighbouring countries remained at risk and should maintain surveillance, laboratory readiness and cross-border coordination.
The delegation subsequently travelled to Bunia, the epicentre of the outbreak in Ituri Province, where it met provincial authorities, health workers, community leaders and response partners.
It also visited the Rwangole Ebola Treatment Centre to assess its readiness to expand access to timely and quality care.
The delegation stressed that communities would play a central role in containing the outbreak, urging authorities to ensure that residents receive accurate information from trusted sources and can report suspected cases and seek treatment without fear.
It also identified community, religious, women and youth leaders as critical partners in building confidence and ensuring that response measures reflect local realities.



CARICOM assesses regional capacity to produce four key products

Trump Rules Out Iran Deal as US Weighs Fresh Military Strikes

Trump’s fuel price cuts face hurdles ahead of midterm elections

Pastor Jerry Eze Defends Miracles At UK Conference Amidst Criticism And Controversy

Diaspora Watch 20th Edition (October 14-20, 2024): Your Trusted Source for Global News and Insights

Tanzanian Man Reportedly Dies And Returns To Life Six Times


-

 Analysis4 days ago
Africa’s Resources Must Build Africa, by Alabidun Shuaib AbdulRahman
-

 Diplomacy3 days ago
UK, Germany ratify defence treaty amid Russian threat
-
 News3 days ago
Trump’s fuel price cuts face hurdles ahead of midterm elections
-

 News4 days ago
Riyadh Airport Attacks Threaten Oil, Global Trade
-
 News3 days ago
Trump Rules Out Iran Deal as US Weighs Fresh Military Strikes
-

 Analysis4 days ago
Nigeria’s 2027 Elections and the Unfinished Business of Diaspora Voting, by Boniface Ihiasota